Thursday, February 10, 2011

Notes of MRI talks at ISC 2011 by Michael Lev and by Greg Albers


These two talks demonstrate patients for whom intervention is NOT likely to help.
* BASIS (reference here: http://www.ajnr.org/cgi/reprint/29/6/1111 )
Lev
1.  Contrary to hypothesis, mismatch IS NOT discriminatory regarding clinical outcome after recanalization.  Most all M1 occlusions with small admission DWI have mismatch, but not all respond to therapy.  The independent outcome predictors, are, NIHSS <= 10 and BASIS* negative have good outcomes, NIHSS > 10 and BASIS + have poor outcomes  and those with one or other are intermediate.
2.  What you need to know, basically, is the amount of core infarct less than 70 cc.  If so, recanalization can be of benefit. You can measure this best, through DWI although CT can be used (see notes below).
3. The other thing you need to know is that a corresponding perfusion deficit exists.  These 2 criteria by MRI are specific but not sensitive for core.
4.  Idea of time is brain uses clock that starts with imaging of a DWI lesion less than 70 cc, not onset of symptoms. 
5.  Yoo Aj et al. Stroke 2010.  DWI and MTT volumes predicts outcome > mismatch.  DWI > 72 ml and NIHSS > 20 are associated with a poor outcome.  MTT < 47 mL and NIHSS < 8 have good outcome.  Combining gives prognosis over 70 %, much better than NIHSS alone (43 %) or imaging alone (54 %).
6.  Protocol is to do noncontrast head CT, then a CTA, then a DWI and only do CT perfusion if patient is not able to get a MRI.  Also notes current focus on radiation.
7.  Uses above characteristics to assess wake up strokes.
8.  Good collaterals is highly specific for small DWI
9.  THRESHOLDED CBF IS LESS VARIABLE THAN CBV AND IS MORE SENSITIVE FOR SALVAGEABLE BRAIN (CBV MORE SPECIFIC).  CT CBF NOT CBV IS "NEXT BEST THING" IF DWI IS NOT AVAILABLE TO DETERMINE SIZE OF CORE.  However there are issues with CT including luxury perfusion, standardization, post-processing and others.
ALBERS TALK
Discusses DEFUSE trial and adds that he criticizes Lev's talk because there is ANOTHER group of patients who do badly with recanalization and that is those with very large perfusion deficit even with a tiny DWI deficit who have a "malignant pattern" of infarct who will do much worse if treated.  A discussion ensued and Wade Smith mentioned a case with a "so-called malignant pattern" who was observed deteriorating, was promptly treated, and got better, therefore felt clinical part was important.  Again mismatch was overrated and not key.
Albers also spoke of converging evidence that > 5.5 or 6 seconds for contrast to reach brain was a threshold of very sick brain.  He also mentioned a case where one branch was not recanalized, but the branch that was recanalized reperfused dead tissue. 
Wade Smith talk
Many points not mentioned. Of interest he thinks IMS 3 is going to really open up intervention therapies.

Grotta talk "Extending reach of tpa eligibility"

presented at Genentech submeeting by Dr Grotta.    A few of his ideas

1.  We need to relax many of the criteria for i-v tpa so that 10-20 percent of patients get drug.  What IS needed to give drug is:  NIHHSS, time of onset, plain CT head, (no CTA till after infusion started), history of bleeding, seziures, surgery, stroke, meds, glucose, platelets and HCT.   NO Foley, CXR (unless suspicion of dissection), ECHO or INR unless on warfarin or heparin

2.  At his center, he has experience treating patients with wake-up strokes with success middling between placebo and standard 0-3 hour patients.

3.  Grotta believes that just as trauma is tiered into level one and two, so should stroke, and patients with level one stroke should be sent to comprehensive, not primary stroke centers where they can get better care.  The scale utilized could be one that differentiates likelihood of major vessel occlusion, the Los Angeles...... scale.

4. His research includes tpa followed by arbogatran, and TCD and hypothermia.

 
neurodoc

Monday, February 07, 2011

another opinion, references on cilostazol

A brief pubmed search about the topic showed a few studies and reviews on the subject. It appears that Cilostazol is non-inferior to aspirin per one study, and is effective in lowering cerebrovascular events with low rates of bleeding. I did not come across any studies that mention adverse events from using this drug. However, since it is not considered standard of care, it probably should only be used on an experimental basis with documentation as such- if it is used at all. Hope this helps.
Lancet Neurol. 2010 Oct;9(10):959-68. Epub 2010 Sep 15.
Cochrane Database Syst Rev. 2011 Jan 19;1:CD008076
J Stroke Cerebrovasc Dis. 2009 Nov-Dec;18(6):482-90.
 

Sunday, February 06, 2011

cilostazol and stroke in Asians

Cochrane Database Syst Rev. 2011 Jan 19;1:CD008076.

Cilostazol versus aspirin for secondary prevention of vascular events after stroke of arterial origin.

Kamal AK, Naqvi I, Husain MR, Khealani BA.

Stroke Service, Section of Neurology, Department of Medicine, Aga Khan University Hospital, Stadium Road, PO Box 3500, Karachi, Pakistan, 74800.

Abstract

BACKGROUND: Aspirin is widely used for secondary prevention after stroke. Cilostazol has shown promise as an alternative to aspirin in Asian people with stroke.

OBJECTIVES: To determine the relative effectiveness and safety of cilostazol compared directly with aspirin in the prevention of stroke and other serious vascular events in patients at high vascular risk for subsequent stroke, those with previous transient ischaemic attack (TIA) or ischaemic stroke of arterial origin.

SEARCH STRATEGY: We searched the Cochrane Stroke Group Trials Register (last searched September 2010), the Cochrane Central Register of Controlled Trials (CENTRAL) (The Cochrane Library 2009, Issue 4), MEDLINE (1950 to May 2010) and EMBASE (1980 to May 2010). In an effort to identify further published, ongoing and unpublished studies we searched journals, conference proceedings and ongoing trial registers, scanned reference lists from relevant studies and contacted trialists and Otsuka Pharmaceutical Co Ltd.

SELECTION CRITERIA: We selected all randomised controlled trials (RCTs) comparing cilostazol with aspirin where participants were treated for at least one month and followed systematically for development of vascular events.

DATA COLLECTION AND ANALYSIS: Data extracted from eligible studies included: (1) a composite outcome of vascular events (stroke, myocardial infarction or vascular death) during follow up (primary outcome); (2) separate outcomes of stroke (ischaemic or haemorrhagic, fatal or non-fatal), myocardial infarction (MI) (fatal or non-fatal), vascular death and death from all causes; and (3) main outcomes of safety including any intracranial, extracranial or gastrointestinal (GI) haemorrhage and other outcomes during treatment follow up (secondary outcomes). We computed an estimate of treatment effect and performed a test for heterogeneity between trials. We analysed data on an intention-to-treat basis and assessed bias for all included studies.

MAIN RESULTS: We included two RCTs with 3477 Asian participants. Compared with aspirin, cilostazol was associated with a significantly lower risk of composite outcome of vascular events (6.77% versus 9.39%, risk ratio (RR) 0.72, 95% confidence interval (CI) 0.57 to 0.91), and lower risk of haemorrhagic stroke (0.53% versus 2.01%, RR 0.26, 95% CI 0.13 to 0.55). In terms of outcome of safety compared with aspirin, cilostazol was significantly associated with minor adverse effects (8.22% versus 4.95%, RR 1.66, 95% CI 1.51 to 1.83).

AUTHORS' CONCLUSIONS: Cilostazol is more effective than aspirin in the prevention of vascular events secondary to stroke. Cilostazol has more minor adverse effects, although there is evidence of fewer bleeds.

PMID: 21249700 [PubMed - in process]

Thursday, December 30, 2010

Pearls on Intracranial atherosclerosis

Turan TN, Chimowitz MI.  . 10 questions about intracranial atherosclerosis.The Neurologist. 16:6 400-405 1020.

1.  MRA and TCD have high negative predictive values but low positive predictive values for detecting intracranial stenosis.  (86-91. v. 36-59 % respectively).  They are therefore adequate screening tests but need CTA for diagnosis or catheter angiography.  CTA studies have limited statistical power therefore catheter studies are the "gold standard" to determine the degree of stenosis, but also confer risk.  A single preliminary study showed CTA had a sensitivity and specificity to detect intracranial stenosis greater than 50 % of of 97.1 and 99.5 % respectively.  In ACAS the risk of stroke with catheter angiography was 1.2 %. The SONIA study was the study that helped evaluate the above.

2.  The risk of stroke with intracranial stenosis is the highest of any stroke subtype, with respect to symptomatic stenosis  of greater than 50 %.  The risk of ischemic stroke in any territory within two years was 20 % in aspirin arm and 17 % in the warfarin arm (WASID).  Over 70 % of strokes occurred in the same territory.  Thus the risk in the symptomatic artery was 15/13 % in aspirin and warfarin arms respectively.  This is higher than the risk with atrial fibrillation or cardioembolic stroke.

3.   The risk of stroke was proportional to the severity of stenosis (risk of stroke within the symptomatic artery occurred in 6/18 % of patients, respectively, with < 70 and >70 % stenosis. 

4.  Other risk factors for stroke in the territory included recent symptoms, female gender, and baseline NIHSS >1.  Vertebrobasilar arterial disease was NOT a risk factor. 

5.  Asymptomatic stenosis was very low risk, with a one year risk of stroke of 0 % in one study and 3.5 % in WASID by MRA. 

6.  "Antithrombotic failures" ie patients already on antiplatelet drugs at time of their stroke, were not at higher risk for recurrent stroke than patients who were not on antiplatelet drugs at the time of their qualifying event. 

7.  Most important risk factors for recurrent stroke were dyslipidemia and hypertension  (SBP> 140). 

8.  SSYLVIA (stenting of symptomatic atherosclerotic lesions in the vertebral or intracranial arteries) was a ph I study of a bare metal stent that showed technical success and a 10.9 % stroke rate in one year with all strokes within the same artery. 

9.  SSAMPRIS study is ongoing (Stenting and Aggressive Medical Management of for Prevention of Recurrent Stroke in Intracranial Stenosis) NIH sponsored study.  In 764  patients it compares angioplasty and stenting plus aggressive medical management v. medical management alone in patients with 70-99 % stenosis.  Patients must have a TIA or nondisabling  stroke within 30 days in an appropriate artery to be eligible.  The protocol includes ASPIRIN for duration, plavix for first 90 days, aggressive bp and lipid management.

10.  See http://www.ssampris.org/ or http://www.sammpris.org/.

Saturday, December 18, 2010

HINTS to diagnose stroke in acute vestibular syndrome: 3 step oculomotor exam

 
Stroke. 2009 Nov;40(11):3504-10. Epub  2009 Sep 17.
HINTS to diagnose stroke in the acute vestibular syndrome: three-step bedside oculomotor examination more sensitive than early MRI diffusion-weighted imaging.
Kattah JC, Talkad AV, Wang DZ, Hsieh YH, Newman-Toker DE.
Department of Neurology, The University of Illinois College of Medicine at Peoria and the Illinois Neurological Institute at OSF Saint Francis Medical Center, Peoria, Ill, USA.

Abstract
BACKGROUND AND PURPOSE: Acute vestibular syndrome (AVS) is often due to vestibular neuritis but can result from vertebrobasilar strokes. Misdiagnosis of posterior fossa infarcts in emergency care settings is frequent. Bedside oculomotor findings may reliably identify stroke in AVS, but prospective studies have been lacking.
METHODS: The authors conducted a prospective, cross-sectional study at an academic hospital. Consecutive patients with AVS (vertigo, nystagmus, nausea/vomiting, head-motion intolerance, unsteady gait) with >or=1 stroke risk factor underwent structured examination, including horizontal head impulse test of vestibulo-ocular reflex function, observation of nystagmus in different gaze positions, and prism cross-cover test of ocular alignment. All underwent neuroimaging and admission (generally <72 hours after symptom onset). Strokes were diagnosed by MRI or CT. Peripheral lesions were diagnosed by normal MRI and clinical follow-up.
RESULTS: One hundred one high-risk patients with AVS included 25 peripheral and 76 central lesions (69 ischemic strokes, 4 hemorrhages, 3 other). The presence of normal horizontal head impulse test, direction-changing nystagmus in eccentric gaze, or skew deviation (vertical ocular misalignment) was 100% sensitive and 96% specific for stroke. Skew was present in 17% and associated with brainstem lesions (4% peripheral, 4% pure cerebellar, 30% brainstem involvement; chi(2), P=0.003). Skew correctly predicted lateral pontine stroke in 2 of 3 cases in which an abnormal horizontal head impulse test erroneously suggested peripheral localization. Initial MRI diffusion-weighted imaging was falsely negative in 12% (all <48 hours after symptom onset).
CONCLUSIONS: Skew predicts brainstem involvement in AVS and can identify stroke when an abnormal horizontal head impulse test falsely suggests a peripheral lesion. A 3-step bedside oculomotor examination (HINTS: Head-Impulse-Nystagmus-Test-of-Skew) appears more sensitive for stroke than early MRI in AVS.

neurodoc

Wednesday, December 15, 2010

Patient foramen ovale

Kent DM, Thaler DE.  Is Patent foramen ovale a modifiable risk factor for stroke recurrence?Stroke 2010: 41 (supplement 1) S 26-S30.

Authors make statistical arguments about PFO management.  Facts that form a basis:

1.  PFO occurs in 25 % of autopsies.
2.  PFO occurs in a higher rate in cryptogenic stroke, but in at least 33 % of strokes with PFO the PFO is incidental.
3.  PFO in Cryptogenic Stroke Study (PICSS) shows near identical stroke recurrence risk in patients with cryptogenic stroke whether or not they have a PFO.  Further, small PFO's had a higher recurrence rate than large ones.  This simply indicates, however, that PICSS included patients who were eventually given a TEE , even if they had a different defined mechanism for their stroke.  Other occult mechanisms such as occult afib or subthreshold aortic atherothrombotic disease may have a higher recurrence rate.
4.  Consistently, studies show that patients with cryptogenic stroke and PFO have less conventional stroke risk factors than patients without PFO.  Since recurrence risk of stroke is about equal in PFO + and - patients, PFO singlehandedly compensates for lack of other risk factors.  Therefore, PFO IS a risk factor for stroke.  Younger patients without DM or HTN are much more likely to have a PFO. 
5.  When a PFO is found in setting with an atrial septal aneurysm, the PFO is rarely incidental to the stroke.
6.  "PFO propensity" is likelihood based on age or other factors that a CS patient has a PFO.  A higher PFO propensity correlates with a lower chance of incidental PFO.  A younger patient without other risk factors may have a very high PFO propensity and therefore probability of nonincidental PFO. 
7.  The margin of benefit in PFO closure is narrow.  Even a low rate of procedure complications could nullify benefit.  "Testing the procedure (closure) in a population in which many incidental PFOs occur may falsely suggest the procedure is of no benefit."

Tuesday, August 03, 2010

Blackbox contraindication intravenous nimodipine

August 2, 2010 — As if a "black box" warning currently on the label were not enough to get anyone's attention, today the US Food and Drug Administration (FDA) again reminded clinicians that nimodipine (Nimotop; Bayer Pharmaceuticals) should be given only by mouth or through a feeding tube and never by intravenous (IV) administration, a method that could be fatal.

Nimodipine, available only as an oral capsule, is used in critical-care settings to treat neurologic complications from subarachnoid hemorrhage.

The FDA states that it continues to receive reports of IV administration of the drug, which sometimes has resulted in death or near-death events. Intravenous administration of nimodipine can cause cardiac arrest, dramatic drops in blood pressure, and other cardiovascular adverse events, according to the agency.

In 1996, Bayer added a bolded statement to the drug's label to warn against incorrect administration after 1 patient who received nimodipine the wrong way died. In 2006, the company added a boxed warning against giving nimodipine intravenously or by other parenteral routes.

Through its Adverse Event Reporting System (AERS) and other sources, including published literature, the FDA has identified 31 cases of nimodipine errors between 1989 and 2009, with 25 involving the prescription or administration of the drug intravenously. Four patients who received nimodipine intravenously died while another 5 came close. One patient suffered permanent harm, according to the agency.

Errors Sometimes Occur With Patients Who Cannot Swallow Capsule

Sometimes nimodipine is administered intravenously despite repeated warnings to the contrary when a patient is not able to swallow the capsule. Such patients are supposed to receive it through a nasogastric tube. The drug comes with instructions for making a hole in both ends of the capsule with a standard 18 gauge needle, removing the contents with a syringe, and emptying the syringe into the tube.

The agency noted that because a standard needle will not fit on an oral syringe, it must be attached to an intravenous syringe. "The use of intravenous syringes to deliver nimodipine increases the chance that the medication will be given intravenously instead of by mouth or nasogastric tube," the FDA stated.

Clinicians can minimize confusion in these circumstances by labeling the syringe with the words "Not for IV Use" and removing the needle, according to the agency. They then should empty the syringe contents into the nasogastric tube followed by 30 mL of normal saline.

More information about today's announcement is available on the FDA's Web site.

To report adverse events related to nimodipine capsules, contact MedWatch, the FDA's safety information and adverse event reporting program, by telephone at 1-800-FDA-1088, by fax at 1-800-FDA-0178, online at http://www.fda.gov/medwatch, or by mail to MedWatch, FDA, 5600 Fishers Lane, Rockville, Maryland 20852-9787.

Friday, July 16, 2010

Mendelsohn maneuver for stroke

The Mendelsohn maneuver is taught by having the patient place


their fingers lightly over the thyroid cartilage and then trying to

swallow. When the thyroid cartilage reaches the top part of its

elevation during the swallow the patient is supposed to try to keep it

in this position for a second or two. The crycopharyngeus upper

esophageal sphincter is stretched by this excursion and is mechanically

opened. There may also be some reflex inhibition of the sphincter, but

the benefit is probably mostly mechanical. Logeman's book on dysphagia

has a much better description.

Tuesday, May 04, 2010

Homocystinuria and stroke

Testai FD, Gorelick PB.  Hommocystinuria, organic acidurias and urea cycle disorder.  Arch Neurol 2010; 67: 148-153.

Features of homocystinuria
Genetics (classical) Aut rec, chromosome 21, deficient cystathione synthase, 90 + mutations, elevated Homocystine and metabolite, methionine(or elevated homocysteine and normal methionine with MTHFR mutations or errors of B12 metabolism. Levels are over 100
. Stroke is due to atherosclerosis, dissection, or SVD

Clinical  -- myopia, osteoporosis, mental retardation, decreased pigmentation of hair and skin, downwards ectopic lenses, dolichostenomelia, and if untreated, seizures, psychiatric disorders, thromboembolic events (PE, MI, stroke).  Clinically there is an equal distribution of the milder B6 (pyridoxal phosphate) responsive form and more severe unresponsive form. 

Thromboembolic events-- distribution-- 51 % peripheral vein (one fourth PE's), 32 % strokes, 11 % peripheral arterial, 4 % MI, 2 % other. 25 % stroke by age 15, half by age 30.  Treatment of pyrodoxal phosphate responders delays first event.

Mechanism-- of thromboembolism is multi.  Increased homocysteine causes premature atherosclerosis due to endovascular dysfunction due to deficient nitrous oxide and oxidative stress.  Also, hypercoagulability due to increased thrombosis and platelet activation may affect stability of arterial wall and cause dissections, arterial thrombosis, and arteriopathy mimicking FMD.

Diagnosis-- Based on clinical and lab features.  Brand reaction is screening test using urinary cyanide nitroprusside.  Blood usually has elevated homocysteine and methionine and decreased cysteine.  Urine excretion of homocysteine, homocystine (the oxidized form) and methionine occurs.  Cystathionine B synthase cultures in fibroblasts, amniotic fluid and chorionic villi can be assessed.

Treatment-- judicious use of B6 (300-600 mg/day) to prevent PN.  Folate, betaine and B12 cause conversion of homocysteine to methionine.  A methionine free diet with cysteine supplementation is suggested. Vitamin C and antiplatelet agents are commonly used.

Saturday, April 10, 2010

Aneurysm presentation-- random clinical pearls


Diagnosis
1.  Of patients with the worst headache of their life, ten percent have aneurysms
2.  Sensitivity of LP to detect aneurysms decreases by seven percent per day
3.  CT-A removes need for catheter angiography in those with more than 5 rbc's
4.  SAH- aneurysmal peaks in April and September and nadirs in June and July
5.  Population prevalence of aneurysm in 2 %
Treatment
6.  **FENESTRATION OF LAMINA TERMINALIS IS EASY, DECREASES HYDROCEPHALUS INCIDENCE FROM 13 TO 2 PERCENT AND ALLOWS LUMBAR DRAINS
7.   EEG is a "pseudoexam " under anesthesia
8.  St Julien NSURG 2008  cardiopulmonary bypass without a chest incision (endovascular)allows fine control of BP and avoids circulatory arrest, hypothermia improves outcomes ( outcome of St Julien)  Grade 0 , 1 (1.5 %), 2 (6.2%), 3 (12.1%), 4 (17.4 %).  CP bypass is good for giant aneurysms
9.  Fisher scale stratifies the risk of vasospasm .  Grade 1: no blood   Grade 2:  vertical layer < 1mm
      Grade 3:    vertical layer > 1 mm, local clot     Grade 4:  ICH/IVH but minimal or no SAH. GRADE  THREE IS MAXIMAL RISK> GRADE FOUR.  Risk of vasospasm is 23 %.   With modified Fisher scale, vasospasm is greatest with grade 4.  About 20-30 % of vasospasms stroke.
10.  Risk of rebleed is 4 % in first 24 hours, then 1-2 % per day for 4 weeks.  Cumulative risk is 20 % at 2 weeks, 30 % at one month, 40 % at 6 months. Ventriculostomy which otherwise can be lifesaving also can precipitate a rebleed.
10.  Risk of rebleed is       

Hemorrhagic shock plus TBI no longer uniformly fatal


Combination is less lethal than formerly provided that CPP is maintained.  Treatment algorithm:  stop bleeding (factor 7), restore volume (whole blood, crystalloid), saline, plasma, platelets, pressors (phenylephrine, vasopressin, norepinephrine, DA), prophylactic phenytoin, for 7 days, treat fevers with tylenol, aggressive nutrition, use hemicraniectomy for impending herniation is efficacious, use GCS to communicate. 

Prehospital care:  avoid hypoxia-- give oxygen, avoid hypotension, hypertonic saline is good; mannitol only if intravascular volume can be maintained, generally avoid hyperventilation unless herniating. 

ICP monitor if GCS < 8 and abnormal CT scan.  Want ICP< 20, intervention threshold around 25.  ICP plateau or A waves are sine qua non of herniation.  These are best seen with changing sweep speed on monitor to minutes.  B waves last from 0.5 to 2 minutes and are associated with changing brain compliance not increased ICP.  C waves are ICP waves associated with respiration. 

Components of a "brain code" are 1) elevated HOB to 45 degrees   2)  HV to pCO2 around 35   3) mannitol .5 grams/kg   4) saline bullet (see    http://neurologyminutiae.blogspot.com/2010/04/saline-bullets-and-hypertonic-saline.html)   5) CSF  drainage

from lecture by Dr Ling

Vasospasm after traumatic brain injury


Unlike its better known couin that occurs after SAH, vasospasm after TBI follows a different time course of 10-21 days is often subclinical and is best treated with nicardipine and endovascular therapy.  It can be monitored with TCD. 

Source-- lecture Col. Geoffrey Ling , MD

Saturday, April 03, 2010

Pearls on blood pressure, misc and hemorrhagic stroke care


1.  PET studies do  not support the concept of an ischemic penumbra, hence blood pressure control should be used judiciously (Schellinger et al, Stroke 2003)

2.  The occurrence of ICH is strongly related to prevailing blood pressure, however no definitive evidence exists that recurrent ICH in the acute setting relates to blood pressure or control thereof (Jauch et al. Stroke 2006)

3.  Intracranial hypertension is associated with a worse outcome

4.  Prior statin use is associated with decreased perihemorrhage edema and decreased 30 day mortality ; however this data is retrospective (Naval et al., 2 refs Neurocritical Care 2008)

5. The Stroke Council continues to advocate for 2-4 weeks of prophylactic antiepileptic therapy in patients with SICH and SAH

6.  Hematoma size (Stoke 1997, Brott et al) and growth (Davis et al, Neurology 2006)  are correlated with mortality

7.  The "spot sign" or contrast extravasation in CTA may identify patients at high risk of hematoma expansion

8.  ICH < 30 cc may benefit from intraclot alteplase

9.  MIS minimal invasive surgery is also considered under investigation although certain types of ICH do not benefit

Sunday, March 28, 2010

Carotid artery webbing

case report at AAN 2010 also known as "atypical FMD" a 41 year old woman with headache  for months, facial droop and aphasia cutely.  MRI showed an M1 occlusion, and delayed time to peak in entire MCA.  Catheter showed bilateral ICA webbing with stagnant flow.  No standard of care is known.

MCA arrow sign in MCA aneursmal SAH

In a review, arrow sign was present in 4 patients with SAH all Fisher 3.  That is 16 % of total MCA aneurysms and was not seen in any other type of aneurysm.

below is an arrow sign for an MCA trifurcation aneurysm (from neurology.org)


Ptosis and astasia with thalamic infarcts: case report (s)

Jain D. et al.  Cerebral ptosis and astasia  "Lateral pulsion" due to a left anterior thalamic lesion.  Mechanisms are reviewed.AAN 2010:PO2:102

Alderazi Y.  Thalamic infarction causing astasia-abasia, ataxia and asterixis.  clinical and radiological features of two cases.  PO2:108.    Wide based gait past pointing and intention tremor on right, with left posterolateral thalamic infarct.    Second case with left arm drift, left asterixis, inability to stand unassisted with right lateral thalamic acute stroke and old left cerebellar hemorrhage. 


Sneddon's syndrome need for angiography

Faris et al.  Sneddon's syndrome without antiphospholipid antibodies:  a report of 26 cases with cerebral angiography (Rabat).  Neurology 2010 74:9:PO2:099.

Authors emphasize Sneddon's syndrome (stroke  plus livedo racemosa) is NOT identical to APL syndrome.  26 patients were studied retrospectively with a combination of focal motor deficits and dementia.  Imaging always showed infarcts with white matter involvement.  Angio showed a distal arteriopathy in 18 cases with pial networks in  cases.  Two had hematomas.  The authors suggested angiography to prevent the unwarranted and dangerous potential use of anticoagulation.

Friday, March 26, 2010

NSE after cardiac arrest during hypothermia predicts outcome

AN 2010 Po1.048  JEF Fugate, Wijdicks et al.  NSE was measured serially in comatose patients undergoing hypothermia.  A cutoff was used of 33 ug/L.  NSE was measured at day one and day three,  with higher NSE suggesting poor prognosis (defined as one year mortality).  48 patients, 41 had first day NSE, 14 had third day NSE.  For first day NSE, the number with high level is given with number of survivors at one year in parenthesis 19 (3) with a low NSE being 22 (11).  Trend in NSE on day 3 was highly predictive (p<.015).  The sensitivity for first day NSE was 59 % for one year mortality with improvement to 66 % if 3 day NSE is included.

Thursday, March 25, 2010

Four score is predictor of outcome in coma after cardiac arrest


Neurology AAN 2010 PO1.045 Wijdicks et al.

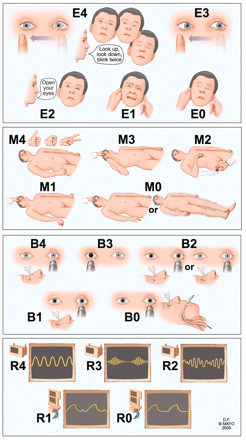
The Four Score differs from the GCS because it has 4 components-- eye, motor, brainstem and respiration (latter two are not included in GCS) .  Prospectively looked at patients from 2006-2009 (n=131) and looked at outcome after one year.  91 died.  31 had four score less than 4 at day one and of these, zero survived.  Of patients with GCS of 3, 4 (7 %) survived at one year.  The Four Score had a specificity for absent survival at one year of 100 % versus 90 % for GCS of 3. 

Description of the FOUR Score


The FOUR score has 4 components: eye responses, motor responses, brainstem reflexes, and respiration pattern. Each component has a maximal value of 4 (Figure 1). Assessing all components of this score usually takes only a few minutes.5 The eye response component of the FOUR score allows differentiation between a vegetative state (eyes open but do not track) and a locked-in syndrome (eyes open, blink, and track vertically on command). The motor assessment component of the FOUR score combines the withdrawal reflex and decorticate rigidity responses because these conditions are often difficult to distinguish clinically. The motor component includes a complex command (the patient is asked to produce a thumbs-up hand signal, a fist, and the peace sign) that determines whether patients are alert.7 Similarly, the motor component of the FOUR score can detect signs of severe cerebral dysfunction, such as myoclonic status epilepticus. Such dysfunction is often a poor prognostic sign for patients with suspected anoxic brain injury.8 The brainstem components of the FOUR score assess the pons, the mesencephalon, and the medulla oblongata in various combinations. The FOUR score also includes an assessment of Cheyne-Stokes respiration and irregular breathing; such signs can indicate bihemispheric or lower brainstem dysfunction of respiratory control. For patients who have undergone intubation, the FOUR score records the presence or absence of a respiratory drive.

FIGURE 1.


Description of Full Outline of UnResponsivenes (FOUR) score. Eye response: E4 = eyelids open or opened, tracking, or blinking to command; E3 = eyelids open but not tracking; E2 = eyelids closed but open to loud voice; E1 = eyelids closed but open to pain; E0 = eyelids remain closed with pain. Motor response: M4 = thumbs-up, fist, or peace sign; M3 = localizing to pain; M2 = flexion response to pain; M1 = extension response to pain; M0 = no response to pain or generalized myoclonus status. Brainstem reflexes: B4 = pupil and corneal reflexes present; B3 = one pupil wide and fixed; B2 = pupil or corneal reflexes absent; B1 = pupil and corneal reflexes absent; B0 = absent pupil, corneal, and cough reflex. Respiration pattern: R4 = not intubated, regular breathing pattern; R3 = not intubated, Cheyne-Stokes breathing pattern; R2 = not intubated, irregular breathing; R1 = breathes above ventilatory rate; R0 = breathes at ventilator rate or apnea.

Sunday, March 21, 2010

The Broken Heart Syndrome

llan Wittstein has published and given lectures and states there are clinical criteria, diagnostic criteria and treatment and prognosis information that can be readily identified. Synonyms include neurogenic stunned myocardium, acute coronary syndrome, stress myocarditis, and Takotsubo syndrome (named after the japanese pot used to capture octopus).  The syndrome is a REVERSIBLE disorder with very abnormal EKG, U waves, ST elevations, Q waves, elevated troponins, normal coronaries on cath, and return of EF to normal within days to weeks.  The pathology includes contraction band necrosis in myocardium, and is linked to hypersympathetic state.  It is a huge problem involving 2 percent of patients undergoing cath and 5-7 % of women.  Most patients are postmenopausal Caucasian women with risk factors who present with chest pain and shortness of breath.  Many have mood disorders


Diagnostic criteria are divided into "helpful" and "required"
HELPFUL-
1.  Acute trigger-- could be emotional (anxiety, joy, grief, fear, anger) or physical (procedure, respiratory drugs) even surprise party. 
2.  Characteristic EKG-- presenting EKG has steep ST elevation without reciprocal changes, T wave inversions everywhere, QT prolongation,  that becomes milder within 2-4 days
3.  Troponin elevation is mild-- less than 5, never more than 20

REQUIRED
1.  Absent coronary thrombosis
2.  Wall motion abnormalities extend beyond a single coronary artery territory  ( 3 patterns:  apical, basal, and midventricular)
3.  Rapid recovery of systolic function within 2 weeks at most

Diagnostic tests that are helpful (but possibly hard/unlikely to obtain esp. acutely)
1.  MRI heart unlike ECHO differentiates dead and stunned tissue.  Dead cardiac tissue lights up with Gadolinium but stunned heart will not

Therapy:
1.  supportive-- possibly not in ICU- arbs, ACEi's, diuretics.  Anticoag if apex not moving to prevent clot kicking, avoid pressors (catechols are a problem)
2.  Balloon pump better than pressors
3.  HHH  good for brain, bad for heart

Prognosis
1.  recurrence 3-10 percent with 2 % mortality
2.  Death is due to etiology not to cardiac dysfunction per se.

Pathophysiology
contraction band necrosis- direct myocyte injury related to calcium overload.

air embolism and air travel

The Neurologist 2010   A  62 year old woman with cerebral artery air embolism during commercial air travel.  16: 136-137.
 
Notes
usual list of associations with air embolus-- surgery, scuba diving, induced abortion, angiography and pneumothorax, orogenital sex on a woman with cerebral air emboli (see Crit Care Med 1988).

A new one is air travel.  In this case, pulmonary bullae due to emphysema occurred as the bullae expanded as the pressure in the cabin was reduced, leading to rupture of the bullae, pneumothorax and air embolism.  Barotrauma was presumably the proximate cause.

Pearls on pediatric strokes

hat tip to Lori Jordan MD JHU


1.  Strokes in kids are as common as brain tumors, about 2-3/100,000
2.  In children ICH = bland infarcts, different than adults (Fullerton, Neurology, 2003).  ICH is often due to AVM's
3.  Among bland infarcts, 25-35 % are cardioembolic, 25 % are dissections, other unusual causes include moya moya, sickle cell disease, HIV and varicella (not in order).
4.  Subarachnoid hemorrhage in kids is usually aneurysmal
5.  Kids at risk often have an inciting event such as trauma or surgery
6.  Kids have a high risk of delay in diagnosis
7.  Sicklers have 10 % stroke, but 20 % more of silent stroke; with SCA and CVA stat consult Hematology for transfusion
8.  Many barriers to alteplase use exist, including diagnosis, , lack of evidence and mimics, and delays, but document why alteplase is not given
9.  MERCI and multi MERCI are not studied in kids
10.AHA guidelines for pediatric stroke published Stroke 2008
11.  Presentation in children is much more likely to include seizure (25 % v. 5 % in adults)
12 . Suggested eval: MRI, MRA H/N, hypercoagulability workup complete, TTE/bubble, HB electropheresis, HIV,
13 references
Roach ES, Golomb MR, Adams R, Biller J, Daniels S, Deveber G, et al.
Management of stroke in infants and children: A scientific statement from a
special writing group of the american heart association stroke council and the
council on cardiovascular disease in the young. Stroke 2008;39:2644-91.
• Amlie-Lefond, C. et al. Use of alteplase in childhood arterial ischaemic stroke: a
multicentre, observational, cohort study. 2009: Lancet Neurol. 8, 530-536.
• Jordan LC, Johnston SC, Wu YW, Sidney SS, Fullerton HJ. The importance of
cerebral aneurysms in childhood hemorrhagic stroke: a population-based study.
Stroke 2009;40:400-405.
• Beslow LA, Licht DJ, Smith SE, Storm PB, Heuer GG, Zimmerman RA, Feiler
AM, Kasner SE, Ichord RN, Jordan LC. Predictors of outcome in childhood
intracerebral hemorrhage: a prospective consecutive cohort study. Stroke 2009;

Wednesday, March 17, 2010

CAA with vasculitis and edema responsive to steroids references

inflammation related CAA as described in : Ann Neurol 2004; 55: 250-256; Brain 2005; 128: 500-515; Neurology 2007; 68 (17); 1411-1416.

Sunday, March 07, 2010

ISC Abstract highlights 2010 San Antonio (pruned and edited)

1.  Restrepo et al. (UCLA) Stroke pretreatment screening for fast Mag trial, involved a 90 second screen with a neurologist, focused, 72 % of patients so diagnosed had acute ischemic stroke, 24 % ICH, rest other

2.  Albright et al. (Penn) studied the potential for the use of air ambulances to increase availability of services and found The combination of pre-hospital regionalization & air ambulance transport of acute stroke
patients would reduce the 135.7 million Americans without 60 minute access to a PSC by
half, to 62.9 million.

3.  Kleindorfer et al. (Cincinatti) stratified t-PA eligibility by age and found contrary to hypothesis, the eligibility for rt-PA significantly increased with increasing age.
Age-Based Eligibility for and Treatment with Rt-PA
Age of Pt           #  Patients           % Eligible for rt-PA  % of Eligible Treated
18–44                   97                        4 (4.1%)              2 (50.0%)
45–54                 219                       15 (6.8%)             5 (33.3%)
55–64                 320                       21 (6.6%)            12 (57.1%)
65–74                 392                       32 (8.2%)            20 (62.5%)
75–84                 502                       47 (9.4%)             23 (48.9%)
85                       300                       29 (9.7%)             10 (34.5%)
Total                  1830                     148 (8.1%)             72 (48.6%)

4.  Riccio et al (Buenos Aires) Occult v. non -occult AF compared in TIA and AIS. Age, female gender and left atrial area (LAA) are traditional determinants of AF.  Out of 194 patients, there were 36 with known AF and 24 with occult AF.  Patients with occult AF were younger, showed a higher proportion of males, had
a smaller LAA, and had more severe strokes. Traditional determinants of AF were associated
with known AF.Diabetes was associated with occult AF.

5.   Gupta et al. (multicenter) General anesthesia during stroke resulted in worse outcomes.

Sunday, February 07, 2010

Infective endocarditis and stroke: pearls

.  The classic triad of infective endocarditis and stroke of fever, murmur and acute neurologic deficit is uncommon, occurring in less than half of patients, with murmur occurring in less than one third (due to decline of valvular disease as a cause) ; fever, embolism and high sed rate may also be seen in NBTE, arteritis with PAN, other rheumatologic disease, or atrial myxoma. 


2.  Organisms are more diverse than previously with Streptococcus representing only 60 percent, including resistant Group D Strep viridans (enterococcus faecalis) and Strep bovis  (associated with GI neoplasia).  Staph aureus is seen in up to 30 % especially those with i-v drug abuse, recent surgery, and no preexisting valve lesion. Patients with prosthetic valves may get S aureus and S epidermidis.  Others, including immunocompromised may get HACEK bacteria and fungi ( hemophilus, actinobacillus, cardiobacterium, Eikinella, Kinzella).  Among pretreated groups, culture negative disease has increased to 5.5 %.


3. Early onset (at presentation of first 48 hours) of neurologic symptoms is more common with Staph aureus than with streptococcal infections, that can occur late (54 v 19 %).  Late embolism is especially common among patients with prosthetic valves (14/15 late strokes in one series had prosthetic valves).  In native valve endocarditis, anticoagulation is of no benefit , certainly for at least 48 hours or until infection is controlled.


4. Cardiac vegetations initially larger than 10 mm are high risk, and are best seen with TEE rather than TTE.  Embolic rate is much higher in presence of visible lesions, and vice versa, visible lesions are much more common among patients with detectable emboli.  The 10 mm size may "open the debate" about the need for valve replacement.


5.  The discovery of endocarditis without emboli does not dictate the cessation of otherwise needed anticoagulant therapy. 


6.  If cardiac surgery is needed, timing is dictated by common sense.  One such protocol is to wait at least five days (until the edema of the stroke has settled) before considering operation, if possible.


7.  Use heparin fairly early on (certainly within 48 hours) of stroke with prosthetic valves with endocarditis, especially if subclinical INR was found on presentation.  Discontinue anticoagulation if possible in most cases of fungal endocarditis.


8.  Intracranial hemorrhage (3-6 % of patients) occurs with aneurysm rupture, septic arteritis, conversion of a bland infarct, and late effects of immune deposition.  Septic bacterial aneurysms may occur at distal branch points, but mycotic aneurysms, large ones, may occur proximally.  However, one study suggested the vast majority of patients with aneurysms had abnormal CT scan.  Present blood on CT or (if headache is present) pleocytosis on CSF examination weighs towards four vessel angiogram. 


9.  Serial angiography is indicated for mycotic aneurysms which may heal  with antibiotics.


10.  Special concern exists among patients with line induced sepsis and bland infarction that could result in late S Aureus superinfection of an initially bland infarct.  Full infective endocarditis treatment regimen may be warranted in these patients and TEE may alternatively show evidence of vegetations. 


Unknown angles
1.  Role of MRA/ CTA
2.  When surgery is required


Tuesday, February 02, 2010

Percentage of patients with stroke with prior TIA

Hackam DG, Kapral  MK, Wang JT et al.  Most stroke patients do not get a warning: a population based cohort study.  Neurology 73: 1074-1075, 2008.

cites data suggesting 17 % of CVA patients have prior TIA.  Authors review 16, 409 charts.  Timing of TIA is not addressed. 12.4  % had prior TIA, but 20% of those with large arter TIA's, much lower with hemorrhagic stroke (5%), somewhat higher with ischemic stroke (15 %).  Risk factors to have prior TIA: older, DM, HTN, AF, CHF,angina, PAD. Patients without TIA were more likely to die in  hospital, arrest, or not be discharged to home. 

Saturday, January 09, 2010

covered stents for carotids

The use of covered stents for the endovascular treatment of extracranial internal carotid artery stenosis: a prospective study with a 5-year follow-up; Szólics A, Sztriha LK, Szikra P, Szólics M, Palkó A, Vörös E; European Radiology
 

OBJECTIVES: To evaluate the safety and feasibility of the use of covered stents for the treatment of extracranial carotid artery stenosis caused by highly embologenic plaques, and to study the long-term outcome of patients receiving such covered stents. METHODS: Between 2002 and 2007, 46 patients (63% symptomatic, 78.3% male, 67 +/- 8.6 years old) with internal carotid artery stenosis caused by embologenic plaques or restenosis were treated with self-expanding covered stents (Symbiot, Boston Scientific). Pre-dilatation or protecting devices were not used. Post-dilatation was applied in every patient. Each patient was followed long-term. The outcome measures were the occurrence of neurological events, and the development of in-stent restenosis, as detected by clinical examination and duplex ultrasound. RESULTS: The technical success rate of stenting was 100%. There were no neurological complications in the peri-procedural period. The mean follow-up period was 34.3 +/- 27.7 months (the rate of patients lost to follow-up was 15.2%) during which no stroke or stroke-related deaths occurred. Restenosis was detected in 3 patients (6.5%). CONCLUSION: Covered stents provide efficient peri- and post-procedural protection against neurological complications due to embolisation from high-risk plaques during carotid artery stenting. Restenosis of covered stents appears to be infrequent during long-term follow-up.

hemodialysis causes cerebral microbleeds in about one fourth

Cerebral microbleeds in predialysis patients with chronic kidney disease; Shima H, Ishimura E, Naganuma T, Yamazaki T, Kobayashi I, Shidara K, Mori K, Takemoto Y, Shoji T, Inaba M, Okamura M, Nakatani T, Nishizawa Y; Nephrology Dialysis Transplantation (Dec 2009)

BACKGROUND: Gradient-echo T2*-weighted magnetic resonance imaging (T2*-weighted MRI) is highly sensitive for detecting cerebral microbleeds (CMBs). CMBs have been reported to be a risk factor for future cerebrovascular events and a marker of cerebral small vessel disease in the general population. Chronic kidney disease (CKD) is an independent risk factor for cardiovascular disease. The relationship between CKD and CMBs, which has not been clarified to date, is examined. METHODS: In this cross-sectional study, T2*-weighted MRI of brain was performed with a 1.5-T MRI system in 162 CKD patients (CKD stages 1-5, excluding CKD stage 5(D)) and 24 normal subjects. RESULTS: CMBs were found in 35 CKD patients (25.6%), but not in control subjects. CMBs were more prevalent in male patients, in those with higher blood pressure, advanced age and poor kidney function. There was a significant association between the prevalence of CMBs and the CKD stage, with higher prevalence of CMBs as the CKD stages advanced (P<0.01). Estimated glomerular filtration rate was a significant factor associated with the prevalence of CMBs, independent of age, gender and hypertension. There was no significant relationship between CMBs and the presence of diabetes mellitus and dyslipidemia. CONCLUSIONS: Decreased renal function is a significant risk factor for CMBs, independent of the presence of hypertension. Poor kidney function could be associated with future cerebrovascular events.

Viagra and stroke

The effect of sildenafil citrate (Viagra) on cerebral blood flow in patients with cerebrovascular risk factors; Lorberboym M, Mena I, Wainstein J, Boaz M, Lampl Y; Acta Neurologica Scandinavica (Dec 2009)


Objectives - Sildenafil citrate is widely used for erectile dysfunction. The present study examined the short-term effects of sildenafil administration in individuals with cerebrovascular risk factors, including patients with a history of stroke. Materials and Methods - Twenty-five consecutive male patients with erectile dysfunction and vascular risk factors were included in the study. A perfusion brain SPECT study was performed at baseline and 1 h after the oral administration of sildenafil. Results - Associations between any of the risk factors and the perfusion scores were not detected, with the exception of stroke. Stroke patients showed significantly more areas with diminished perfusion after sildenafil administration compared to baseline. Conclusions - In patients with diabetes or hypertension, a dose of 50 mg sildenafil does not appear to produce detrimental effects on cerebral blood flow. However, patients with a history of stroke may be at increased risk of hemodynamic impairment after the use of sildenafil.

Sunday, December 06, 2009

avoid plavix plus nexium/prevacid

FDA: Avoid Coadministration of Clopidogrel and Omeprazole, Esomeprazole

SILVER SPRING, Md -- November 17, 2009 -- The US Food and Drug Administration (FDA) has new data showing that the proton pump inhibitor (PPI) omeprazole (Prilosec/Prilosec OTC) reduces the anti-blood clotting effect of clopidogrel (Plavix) by almost half when these 2 medicines are taken by the same patient. Patients at risk for heart attacks or strokes who use clopidogrel to prevent blood clots will not get the full effect of this medicine if they are also taking omeprazole; therefore, the FDA recommends that the coadministration of omeprazole and clopidogrel be avoided.

The new recommendations, updated from a January 2009 Early Communication, are based on study results from the manufacturers of clopidogrel. The studies confirm that coadministration of omeprazole with clopidogrel results in decreased levels of clopidogrel's active metabolite, reducing clopidogrel's anticlotting effect.

Omeprazole inhibits the drug-metabolising enzyme (CYP2C19), which is responsible for the conversion of clopidogrel into its active metabolite. The new studies compared the amount of clopidogrel's active metabolite in the blood and its effect on platelets in patients who took clopidogrel plus omeprazole versus those who took clopidogrel alone. A reduction in active metabolite levels of about 45% was found in those who received clopidogrel with omeprazole compared with those taking clopidogrel alone. The effect of clopidogrel on platelets was reduced by as much as 47% in patients receiving clopidogrel and omeprazole together. These reductions were seen whether the drugs were given at the same time or 12 hours apart.

Since the level of inhibition among other PPIs varies, it is unknown to what amount other PPIs may interfere with clopidogrel. However, esomeprazole (Nexium), a PPI that is a component of omeprazole, inhibits CYP2C19 and should also be avoided in combination with clopidogrel.

Other stomach acid-reducing drugs, such as ranitidine (Zantac), famotidine (Pepcid), nizatidine (Axid), or antacids, are not expected to interfere with the anticlotting activity of clopidogrel because they do not inhibit CYP2C19 activity. However, cimetidine (Tagamet/Tagamet HB) does inhibit CYP2C19 activity and should not be used.

In addition to cimetidine, other drugs that are potent inhibitors of the CYP2C19 enzyme would be expected to have a similar effect and should be avoided in combination with clopidogrel. These include fluconazole (Diflucan), ketoconazole (Nizoral), voriconazole (VFEND), etravirine (Intelence), felbamate (Felbatol), fluoxetine (Prozac, Sarafem, Symbyax), fluvoxamine (Luvox), and ticlopidine (Ticlid).

Sanofi-aventis and Bristol-Myers Squibb, the makers of Plavix (clopidogrel), are updating this drug's label with the details of the studies and are conducting follow-up studies to further explore drug interactions with clopidogrel.

Until further information is available, FDA recommends the following:
• The concomitant use of omeprazole and clopidogrel should be avoided because of the effect on clopidogrel's active metabolite levels and anticlotting activity. Patients at risk for heart attacks or strokes, who are given clopidogrel to prevent blood clots, may not get the full protective anticlotting effect if they also take prescription omeprazole or the OTC form.
• Separating the dose of clopidogrel and omeprazole in time will not reduce this drug interaction.
• Other drugs that should be avoided in combination with clopidogrel because they may have a similar interaction include esomeprazole, cimetidine, fluconazole, ketoconazole, voriconazole, etravirine, felbamate, fluoxetine, fluvoxamine, and ticlopidine.
• At this time the FDA does not have sufficient information about drug interactions between clopidogrel and PPIs other than omeprazole and esomeprazole to make specific recommendations about their coadministration. Healthcare professionals and patients should consider all treatment options carefully before beginning therapy.
• There is no evidence that other drugs that reduce stomach acid, such as most H2 blockers ranitidine (Zantac), famotidine (Pepcid), nizatidine (Axid), except cimetidine (Tagamet and Tagamet HB - a CYP2C19 inhibitor), or antacids interfere with the anticlotting activity of clopidogrel. Ranitidine and famotidine are available by prescription and OTC to relieve and prevent heartburn and antacids are available OTC to relieve heartburn.
• Talk with your patients about the OTC medicines they take. Be aware that patients may be taking nonprescription forms of omeprazole and cimetidine.

The FDA will continue to investigate other drug interactions with clopidogrel. The FDA plans on presenting this issue at the next meeting of the FDA's Drug Safety Oversight Board in November. The Agency will communicate any further recommendations or conclusions once additional information is available.

RELATED LINKS:
PPIs Thwart Clopidogrel's Anticlotting Effectiveness in Diabetics Post Stenting: Presented at ADA

Effectiveness of Clopidogrel May Be Reduced by Common Heartburn Drugs: Presented at SCAI

Certain PPIs Increase Risk of Heart Attacks for Patients on Clopidogrel

SOURCE: US Food and Drug Administration

Wednesday, December 02, 2009

erythropoietin and vasospasm after SAH- synergistic with statins

 J Neurosurg  

Interaction of neurovascular protection of erythropoietin with age, sepsis, and statin therapy following aneurysmal subarachnoid hemorrhage; Tseng MY, Hutchinson PJ, Kirkpatrick PJ; Journal of Neurosurgery (Nov 2009)

    Object In a previous randomized controlled trial, the authors demonstrated that acute erythropoietin (EPO) therapy reduced severe vasospasm and delayed ischemic deficits (DIDs) following aneurysmal subarachnoid hemorrhage. In this study, the authors aimed to investigate the potential interaction of neurovascular protection by EPO with age, sepsis, and concurrent statin therapy. Methods The clinical events of 80 adults older than 18 years and with<72 hours of aneurysmal subarachnoid hemorrhage, who were randomized to receive 30,000 U of intravenous EPO-beta or placebo every 48 hours for a total of 3 doses, were analyzed by stratification according to age (< or≥ 60 years), sepsis, or concomitant statin therapy. End points in the trial included cerebral vasospasm and impaired autoregulation on transcranial Doppler ultrasonography, DIDs, and unfavorable outcome at discharge and at 6 months measured with the modified Rankin Scale and Glasgow Outcome Scale. Analyses were performed using the t-test and/or ANOVA for repeated measurements. Results Younger patients (<60 years old) or those without sepsis obtained benefits from EPO by a reduction in vasospasm, impaired autoregulation, and unfavorable outcome at discharge. Compared with nonseptic patients taking EPO, those with sepsis taking EPO had a lower absolute reticulocyte count (nonsepsis vs sepsis, 143.5 vs. 105.8 x 10(9)/L on Day 6; p = 0.01), suggesting sepsis impaired both hematopoiesis and neurovascular protection by EPO. In the EPO group, none of the statin users suffered DIDs (p = 0.078), implying statins may potentiate neuroprotection by EPO. Conclusions Erythropoietin-related neurovascular protection appears to be attenuated by old age and sepsis and enhanced by statins, an important finding for designing Phase III trials.

Platelets transfusions does not help mortality in mild TBI in ASA/Plavix takers

 Am Surg Does platelet administration affect mortality in elderly head-injured patients taking antiplatelet medications?; Monson B, Butler KL, Fortuna GR, Saxe JM, Dolan JP, Markert RJ, McCarthy MC, Downey DM; American Surgeon 75 (11), 1100-3 (Nov 2009)

    A significant portion of patients sustaining traumatic brain injury (TBI) take antiplatelet medications (aspirin or clopidogrel), which have been associated with increased morbidity and mortality. In an attempt to alleviate the risk of increased bleeding, platelet transfusion has become standard practice in some institutions. This study was designed to determine if platelet transfusion reduces mortality in patients with TBI on antiplatelet medications. Databases from two Level I trauma centers were reviewed. Patients with TBI 50 years of age or older with documented preinjury use of clopidogrel or aspirin were included in our cohort. Patients who received platelet transfusions were compared with those who did not to assess outcome differences between them. Demographics and other patient characteristics abstracted included Injury Severity Score, Glasgow Coma Scale, hospital length of stay, and warfarin use. Three hundred twenty-eight patients comprised the study group. Of these patients, 166 received platelet transfusion and 162 patients did not. Patients who received platelets had a mortality rate of 17.5 per cent (29 of 166), whereas those who did not receive platelets had a mortality rate of 16.7 per cent (27 of 162) (P = 0.85). Transfusion of platelets in patients with TBI using antiplatelet therapy did not reduce mortality.

Saturday, November 28, 2009

Neuropsych and carotid stenosis

M. Silvestrini, MD, I. Paolino, MD, F. Vernieri, MD, C. Pedone, MD, R. Baruffaldi, MD, B. Gobbi, MD, C. Cagnetti, MD, L. Provinciali, MD and M. Bartolini, MD . Cerebral hemodynamics and cognitive performance in patients with asymptomatic carotid stenosis. NEUROLOGY 2009;72:1062-1068
Objective: The aim of this study was to investigate whether the presence of severe internal carotid artery stenosis may be associated with different cognitive performance in relation to the side of the stenosis and its hemodynamic consequences.

Methods: Eighty-three patients with asymptomatic severe unilateral internal carotid stenosis were included. A neuropsychological investigation including Verbal Fluency using phonemic and category access, Coloured Progressive Matrices, and Complex Figure Test Copy was performed. Each patient underwent an assessment of cerebrovascular reactivity (CVR) to hypercapnia with transcranial Doppler ultrasonography using the breath-holding index (BHI). Thirty healthy subjects comparable for demographic characteristics and vascular risk profile served as controls. Subjects with carotid stenosis were classified into two groups: preserved CVR (BHI 0.69), 48 patients (25 with left and 23 with right stenosis); and impaired CVR (BHI <0.69), 35 patients (19 with left and 16 with right stenosis).

Results: Subjects with left stenosis and reduced CVR had significantly lower performances at phonemic verbal fluency with respect to controls and the other groups of stenosis. In subjects with right stenosis and reduced CVR, scores obtained in Coloured Progressive Matrices and in Complex Figure Test Copy were significantly lower with respect to the other groups.

Conclusions: These results suggest that an alteration of cerebrovascular reactivity may be responsible for reduction in some cognitive abilities involving the function of the hemisphere ipsilateral to carotid stenosis. Such findings may be of interest for providing a more comprehensive indication to surgical treatment in subgroups of subjects with asymptomatic carotid stenosis.


Wednesday, October 21, 2009

safety of CT perfusions per FDA

For more information, please see FDA's Safety Investigation of CT Brain Perfusion Scans:  Initial Notification at:

  http://www.fda.gov/MedicalDevices/Safety/AlertsandNotices/ucm185898.htm <http://www.fda.gov/MedicalDevices/Safety/AlertsandNotices/ucm185898.htm>

Monday, October 05, 2009

d-dimer predicts cardioembolic stroke

D-dimer assay may differentiate subtypes of ischemic stroke; study of 126 patients hospitalized with acute ischemic stroke;
stroke subtypes were cardioembolic in 34 (27%),
atherothrombotic in 34 (27%),
lacunar in 31 (25%),
unknown in 27 (21%);

mean D-dimer levels on day 1 were 2.96 mcg/mL with cardioembolic stroke, 1.34 mcg/mL with atherothrombotic stroke and 0.67 mcg/mL with lacunar stroke; similar results at days 6 and 12; D-dimer > 2 mcg/mL had 59% sensitivity and 93% specificity for predicting cardioembolic stroke, D-dimer < 0.54 mcg/mL had 61% sensitivity and 96% specificity for predicting lacunar stroke

(Arch Intern Med 2002 Dec 9/23;162(22):2589)

Sunday, October 04, 2009

Biomarkers for stroke


Foerch C, Montaner J, Furie KL,Ning MM, Lo EH. Searching for oracles: blood biomarkers for acute stroke . Invited Article. Neurology 2009; 73: 393-399.


Article discusses batteries of biomarkers used together to diagnose acute stroke or intracranial hemorrhage. They note that CT excludes hemorrhage, but does not include stroke, so a panel of markers may play a useful role.

To diagnose acute ischemic stroke, authors suggest a need for higher sensitivity than specificity to avoide missing treatable strokes.

NMDA antibodies are typically high early in stroke (first 3 hours) but may be false positive in patients with atherosclerosis or old strokes. New research focuses on fragments of NMDA rather than antibodies.

Reynolds et al. (Clin Chemisty2003) tested 50 markers and found a panel of four or five significantly predicted ischemic stroke. They were S100b, B type neurotropic growth factor, VWF, MMP-9, and monocyte chemotactic protein 1.They had a combined sens/spec of 91/97 for IS within 12 hours of stroke onset. The same group in a 2d study found S100b, MMP-9. vascular adhesion molecule, and VWF to have a combined sens/spec of 90/90. (Lynch JR Stroke 2004). Laskowitz found a panel of BNP, CRP, d-dimer, MMP-9, and S100b has a sens/spec of 81/70. Laskowitz et al. published a prospective multicenter trial (Stroke 2009) of 1100 patients using d-dimer, BNP, MMP-9, and S100b within 24 hours of stroke onset and found a s/s of 86/37.

For intracranial hemorrhage, markers include GFAP, which is also high in gliomas. In another analysis, RAGE and S100b best differentiated group from controls. ApoC1 and especially ApoC3 differentiate ICH from controls.

Montaner et al (Circulation 2003) found that MMP-9 was a powerful predictor of hemorrhagic risk in patients given alteplase. MMP-9 is also a predictor of HT in non lysed patients. Fibronectin has a similar pattern.

S100B which tends to correlate with infarct size, was also a predictor of malignant edema in one study (Foerch et al., Stroke 2004).

Wednesday, September 23, 2009

Bypass, strokes and Lou Caplan's call for action

Caplan LR. Translating what is known about neurological complications of coronary artery bypass graft complications into action. Arch Neurol 2009; 66: 1062-1064.

Dr Caplan editorializes about stroke and CABG and distills knowledge into 3 pages and a number of points that can be bulleted.

1. Complications from bypass are increasing as bypass patients are sicker. In 1994, the rate of stroke and delirium after bypass were 2.9 and 7.7 % respectively, at Johns Hopkins Hospital. In 2004, the respective rates were 4.5 and 13.8 %.

2. There is virtually no relationship between carotid disease, especially asymptomatic, and cardiac risk during bypass. In the large series, 95 % had strokes not in the territory of a diseased carotid artery. Of the four patients who did have strokes in the diseased carotid territory, the carotid was occluded in 3 of 4 so the mechanism was not hemodynamic but embolic.

3, Aortic atheromatosis is the most important cause of stroke after bypass, with cardiac factors second. The use of aortic filters, the use of off pump bypass or avoidance of cross clamping and identifying patients in advance results in improved outcomes. Identifying susceptible patients can be done with TEE, chest x ray, chest CT, or intraoperative epiaortic ultrasound before clamping. Most patients have not had this done.

4. ECHO to look at ventricular contractile function and thrombi is often not done but should be done.

5. Identification of a cardiologist and in some cases, neurologist in house to see patient preop would be helpful.

6. Risk of stroke is highest in those with previous TIA or stroke.

Thursday, September 03, 2009

hypercoagulation profile based on scenario-Oregon

 NEUROLOGY VENOUS THROMBOSIS PANEL:
- Protein C Activity
- Protein S Activity
- Antithrombin Activity
- Activated Protein C Resistance
- Prothrombin G20210A PCR
- Lupus Anticoagulant
- Anticardiolipin IgG and IgM
- Homocysteine

NEUROLOGY ARTERIAL THROMBOSIS PANEL
- Lupus Anticoagulant
- Anticardiolipin IgG and IgM
- Homocysteine
- Lipoprotein (a)

NEUROLOGY ARTERIAL THROMBOSIS PANEL, WOMEN>40
- Lupus Anticoagulant
- Anticardiolipin IgG and IgM
- Homocysteine
- Lipoprotein (a)
- Activated Protein C Resistance
- Prothrombin G20210A PCR

Wednesday, September 02, 2009

Hypercoagulable workup (incl effects warfarin on tests)


hat tip David Gordon, MD Professor/Chairman Neurology at OKL


Hypercoagulable Profile
􀂃 Protein C
􀂃 Protein S free and total
􀂃 Antithrombin III
􀂃 Fibrinogen
􀂃 Factor VII
􀂃 Factor VIII
􀂃 Activated protein C resistance (APCR)
􀂃 Factor V Leiden mutation
􀂃 Prothrombin G20210A mutation
􀂃 Anticardiolipin antibodies
􀂃 Anti-beta-2-glycoprotein I antibodies
􀂃 Antiphosphatidylserine antibodies
􀂃 Lupus anticoagulant
􀂃 Lipoprotein (a)
􀂃 C-reactive protein
􀂃 Methyltetrahydrofolate reductase C677T and A1298C
􀂃 Sickle prep (if African heritage)
Affect of Coumadin on Hypercoagulable Profile
􀂃 Protein C (may be decreased with warfarin)
􀂃 Protein S free and total (may be decreased with warfarin)
􀂃 Antithrombin III (not affected by warfarin)
􀂃 Fibrinogen (not affected by warfarin)
􀂃 Factor VII (may be affected by warfarin)
􀂃 Factor VIII (not affected by warfarin)
􀂃 Activated protein C resistance (must alter methods to compensate for warfarin)
􀂃 Factor V Leiden mutation (not affected by warfarin)
􀂃 Prothrombin 20210 mutation (not affected by warfarin)
􀂃 Anticardiolipin antibodies (not affected by warfarin)
􀂃 Anti-beta-2-glycoprotein I antibodies (not affected by warfarin)
􀂃 Antiphosphatidylserine antibodies (not affected by warfarin)
􀂃 Lupus anticoagulant (screening tests not affected by warfarin, but “mixing studies” to
confirm are affected by warfarin)
􀂃 Lipoprotein (a) (not affected by warfarin)
􀂃 C-reactive protein (not affected by warfarin)
􀂃 Methyltetrahydrofolate reductase C677T and A1298C (not affected by warfarin)
􀂃 Sickle prep (if African heritage) (not affected by warfarin

Saturday, June 06, 2009

North American moya moya is different


Hallemeier et al. Stroke 2006. Authors looked at 34 adults with the condition. 22 had bilateral and 12 unilateral moya moyal vessels. North Americans present more often with ischemic stroke whereas Asians present with hemorrhage more often. 0/12 unilateral patients subsequently developed contralateral symptoms. Symptomatic patients had high levels of recurrence both homolaterally and contralaterally, and asymptomatic patients had a low risk of ischemic events. Surgical treatment revascularization led to less recurrence, with a fairly high perioperative morbidity and mortality ( as high as 17 % for the latter). N American moya moya may be a different entity than the Japanese kind.

Statins prevent vasospasm after subarachnoid hemorrhage


McGirt Mj et al. J Neurosurg 2006; 105: 671-674. (Duke) 115 patients were retrospectively reviewed with multivariate regression analysis. Statin therapy started on admission with SAH resulted in a elevenfold decrease in vasospasm. ACA/ICA aneurysm also was associated with vasospasm. Tseng MY al (Stroke 2005; J Neurosurg 2007) also published 2 articles on the subject . The mechanism is thought to be cholesterol independent, perhaps related to nitrous oxide.

Number to harm with iv tpa


Saver JL Hemorrhage after thrombolytic therapy for stroke. The clinically relevant number needed to harm Stroke 2007; 38: 2279-2283

Author reviews original NINDS data on hemorrhages, n=20/312 patients treated, and noted that they tended to be older, have mass effect on CT, have higher serum glucose, and more severe strokes. The number needed to harm, ie an additional dead or disabled outcome (MRS>= 3) attributable to SICH is 707, based on the expected outcome of these 20 patients.

NNH for dead disabled outcome MRS (.=4) 126, for fatal outcome 36.5, and for worsening of any degree between 30 and 40.

Basic conclusion is that most patients with SICH are destined for bad outcomes from the get go.

IV alteplase plus mutlimerci is safe


Smith WS et al. Safety of mechanical thromobectomy and iv tpa in acute ischemic stroke. Results of the Multi Mechanical Embolus in Cerebral Ischemia (Merci) trial part I. AJNR 2006; 27: 1177- 1182.

Study enrolled patients who either did not receive iv tpa or received it and did not recanalize. It was an international prospective single arm trial up to 88 hours post stroke. 111 patients received the procedure with mean NIHSS of 19 +/= 6.3 30/111 received tpa prior. 60/111 recanalized with retriever alone, 77/111 with adjunctive therapy. 9 % has SICH. 5 % had procedural complications.

Clinical outcomes not given

Blogger note: Like many radiology studies, this one has important limitations. The study does show that Multi Merci is safe and efficacious using recanalization, but fails to look at clinical outcome of the patient. PROACT 2 is the single study showing clinical benefit of interventional therapy for stroke, namely intrarterial lysis.

Warfarin in elderly -- Birmingham study


Mant J et al. for BAFTA investigators. Warfarin v. aspirin in an elderly community population with atrial fibrillation (the Birmingham Atrial Fibrillation Treatment of the Aged Study, BAFTA): a randomized clinical trial

patients: 973 patients 75+ age, mean 81, SD 4 from primary care were randomized to aspirin 75 mg or warfarin with INR target of 2-3, and followed a mean 2.7 years. The endpoint was fatal or disabling stroke, ICH, an arterial embolism.

results: in warfarin group there were 24 events, with 2 ICH and remainder ischemic strokes, in aspirin group there were 48 events. Yearly risk reduction was 3.8 percent in aspirin group, 1.8 percent in warfarin group, risk reduction 2 %, p=0.003. Risk of hemorrhagic events increased 0.2 % in warfarin group, 1.4 to 1.6 percent.

Warfarin is treatment of choice.

Friday, June 05, 2009

Aspirin v. anticoagulation in carotid dissection


Georgiadis D, Arnold M, et al. Neurology 2009; 72:1810-1815

A study of 298 patients with spontaneous Carotid artery dissection

Main points

ischemia is relatively rare after dissection in 3 months ischemic stroke occurred in 0.3 %, TIA 3.4 %, retinal ischemia 1 % with no significant difference between groups. Ischemic events were commoner in those with ischemic events at onset. It is important to separate these two groups. Anticoagulation had a predictable 2 % complication rate. There was 97 % followup with exam or structured telephone interview. In literature review , 2 recent meta analyses showed no difference. (see Cochrane database Syst Rev 2003, and Lyrer et al, Stroke 2004). This was not a RCT, and warfarin was prescribed up to 1997 and aspirin thereafter. The number of patients was too small to evaluate treatment differences. The primary finding was the low rate of strokes after sicd.

Tuesday, May 19, 2009

criteria for alteplase in community setting

from a highly placed stroke neurologist:
IA therapy has already been endorsed as reasonable in selected patients
by AHA/ASA, ACC  -  virtually all comprehensive stroke centers are doing
it. FDA approval is years away and is not required per se. IA case
selection variables have been quasi standardized: NIHSS > 10; major
vessel occlusion (M1/M2 MCA and basilar artery are favored sites for
intervention; carotid T and ICA occlusion somewhat more controversial
but doable); < 6 hours from stroke onset (some argue intervention should
be completed < 8 hours from stroke onset based on PROACT 2 . MERCI
retriever for clot removal is give
n as 8 hours); no standard thrombolytic exclusions. Many would add MR
or CT mismatch imaging as another selection factor especially as
you.approach 6 to 8 hours or in patients > 80 years of age with NIHSS >
20 (no standard criteria yet but 20% mismatch is probably too low; if
you had >50% mismatch and DW volume < 100 cc that would be favorable).
So until and unless you want to randomize into a (nonexistent) clinical
trial you.could simply not do IA (using the specious (in my view)
“unproven” argument) or you could have access to an experienced
comprehensive stroke center and do “drip and ship.”  You could
possibly develop IA at a certified primary stroke center if resources
(angio suite; interventionalist 24/7 etc) were available. Otherwise I do
not advocate IA stroke therapy at community hospitals.